Use a dental practice business plan template to force decisions, not simply produce a polished document. It should explain whom the practice will serve, why the location and service model make sense, what must happen before opening, how cash will be used, and what evidence would cause the owner to change course.
Use the fill-in sections below as a working plan. Replace every bracketed prompt with documented assumptions and sources. A lender may require a particular format and supporting documents. Work with a dental CPA, attorney, lender, broker, insurance adviser, architect, and clinical experts as appropriate; this is an operating template, not financial or legal advice.
One-page dental practice plan
Complete this first, then build the detailed sections.
Practice concept: [One sentence: location, practice type, and patient group] Ownership objective: [What the owner wants to build and why] Primary service area: [Geography and travel assumptions] Patient need: [Evidence of unmet or poorly served demand] Service model: [Core services at launch; what is referred] Differentiation: [Operationally provable difference, not a slogan] Launch path: [Startup, acquisition, partnership, or other] Opening target: [Date range and dependencies] Total uses of funds: [Build-out, equipment, working capital, fees, contingency] Funding sources: [Owner equity, loan, investors if lawful, other] Break-even method: [Defined formula and assumptions] Top three risks: [Risk, leading indicator, mitigation owner] Next 90-day milestone: [Specific evidence required]
If the one-page version is vague, adding 30 pages will not fix it. Resolve the major unknowns first.
Complete the detailed plan
1. Executive summary
Write this section last. Summarize:
- legal and ownership structure under consideration;
- location and premises status;
- target patient groups and evidence of demand;
- launch services and schedule;
- owner and leadership qualifications;
- amount and purpose of funding;
- expected opening period;
- key financial assumptions and downside case;
- decisions or approvals still outstanding.
Avoid guaranteed growth language. Label projections as projections. If a forecast depends on provider capacity, payer participation, construction timing, or credentialing, say so.
2. Practice and ownership model
Describe the planned entity and ownership only after state-specific professional and legal advice. Record who can own the clinical entity, who employs staff, who signs the lease, who holds contracts, and how management services work if multiple entities are involved.
Define the clinical scope at launch. Separate services the owner is trained, licensed, equipped, and credentialed to provide from future possibilities. Include referral relationships and emergency coverage plans at a high level.
Write the patient experience as a sequence: discovery, inquiry, scheduling, forms, arrival, evaluation, treatment planning, financial discussion, follow-up, and recall. This exposes systems the financial model might otherwise miss.
3. Market and competitive analysis
The SBA recommends market research and competitive analysis to find customers and understand competitive advantage. For a dental office, gather evidence rather than relying on a broker's summary:
- population and household trends in the realistic service area;
- employer, school, housing, and transit patterns;
- age and language considerations;
- competing practices and services visibly offered;
- payer and self-pay considerations;
- new-patient access observed through lawful mystery shopping or public information;
- development, zoning, and construction factors;
- referral resources and specialist availability.
Document source, date, geography, and limitations for every figure. A county-wide statistic may not describe a ten-minute drive area. Competitor websites may be outdated. Search visibility is not proof of capacity or production.
Define three patient segments by need and behavior, not stereotypes. For each, record the question that triggers a search, likely barriers, preferred contact path, relevant service, and evidence.
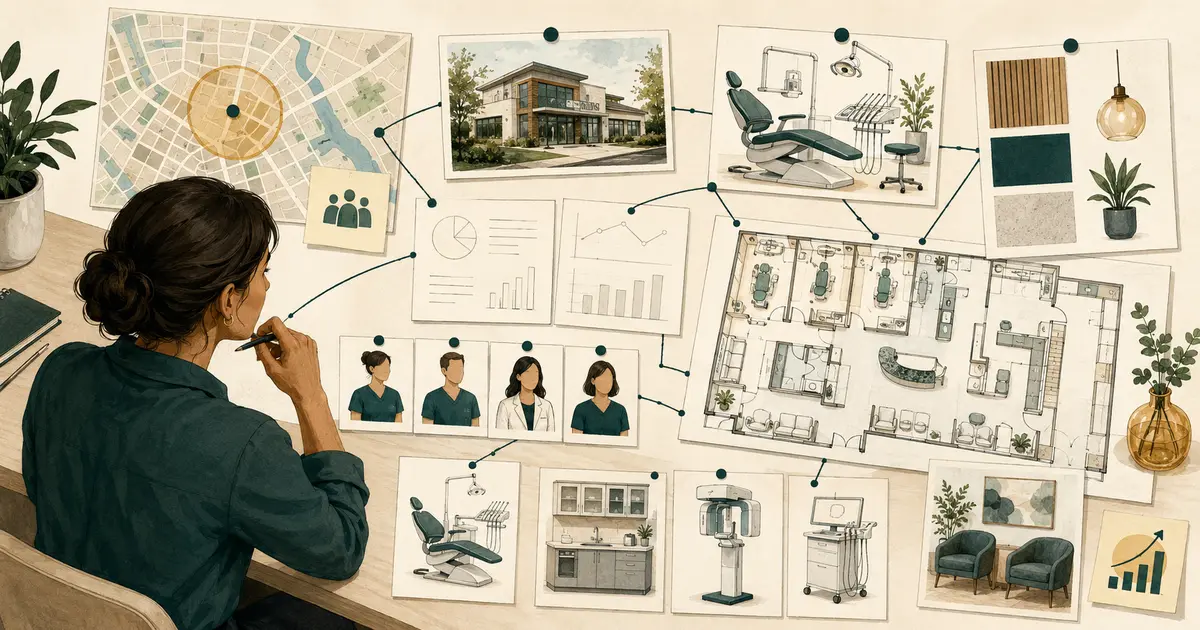
4. Location and facility plan
Create a premises decision table:
| Factor | Requirement | Evidence | Owner | Decision date |
|---|---|---|---|---|
| Permitted dental use | [Requirement] | [Zoning/legal review] | [Name] | [Date] |
| Size and operatory plan | [Range] | [Architect/clinical plan] | [Name] | [Date] |
| Accessibility | [Requirements] | [Professional review] | [Name] | [Date] |
| Utilities and equipment support | [Needs] | [Engineering/vendor review] | [Name] | [Date] |
| Visibility and access | [Criteria] | [Site visits/data] | [Name] | [Date] |
| Lease economics | [Limits] | [Attorney/CPA model] | [Name] | [Date] |
Model rent commencement, free-rent periods, deposits, tenant improvements, personal guarantees, restoration obligations, option terms, delays, and cost overruns. Do not sign a lease based only on an attractive monthly rent.
Coordinate location tasks with a dental office opening checklist so licenses, utilities, technology, hiring, supplies, and patient communications have dependencies and owners.
5. Services, pricing, and payer strategy
List service families, necessary equipment, expected appointment length, clinical staffing, lab dependency, and referral plan. Explain how fees will be developed and reviewed. If the practice expects payer participation, identify credentialing timelines, contract review, fee-schedule analysis, claim operations, and the risk of delayed effective dates.
Do not assume every inquiry becomes an appointment or every appointment becomes collected revenue. Build a documented funnel with scenario ranges. Separate gross charges, contractual adjustments, refunds, bad debt, and cash collections under the CPA's model.
Explain financial communication: estimates, deposits, payment methods, financing relationships, cancellation policy, and who can adjust an account. Marketing should never promise coverage or a final patient responsibility before authorized verification.
6. Marketing and patient acquisition
Choose channels by audience intent, cost, operational readiness, and attribution. The plan might include a complete Google Business Profile when eligible, location and service pages, professional relationships, community participation, educational content, and carefully controlled advertising.
For each channel specify:
Audience: [Who] Message: [Accurate reason to consider the practice] Offer or action: [Call, request, event, download] Budget: [Setup and ongoing] Owner: [Role] Measure: [Qualified inquiries, schedules, kept visits] Stop rule: [Evidence that triggers revision]
Use the dental practice management guide to connect acquisition plans with the team and systems required to answer demand.
7. Team and operating model
Create an organization chart for opening day and the first two hiring stages. For each role, define license or credential requirements, core outcomes, schedule, supervision, training, compensation assumptions, and backup coverage. Obtain employment-law and payroll guidance for classification, pay, breaks, overtime, benefits, and local requirements.
Map daily workflows: opening, scheduling, intake, identity verification, clinical handoffs, checkout, billing, records, privacy incidents, emergency calls, deposits, closing, and downtime. Link every workflow to an owner and training evidence. A dental office SOP template can keep the operating plan from becoming prose no one uses.
8. Financial plan and assumptions
Build three linked views with a dental CPA:
- Startup uses and sources: build-out, equipment, technology, professional fees, deposits, initial supplies, pre-opening payroll, marketing, working capital, and contingency.
- Monthly operating model: appointment capacity, utilization assumptions, collections timing, staffing, lab and supply costs, occupancy, debt service, insurance, technology, and owner compensation.
- Cash-flow model: actual timing of cash in and out, not just accounting revenue and expense.
For every material assumption, add source, owner, date, base case, downside case, and sensitivity. Do not borrow a universal dental overhead percentage and force the practice to match it. Rent, labor, service mix, payer mix, ownership compensation, debt, and accounting definitions vary.
Calculate break-even using consistent definitions approved by the CPA. Stress-test a later opening, slower credentialing, lower schedule fill, construction overrun, equipment failure, and staff turnover. State how much liquidity remains after opening and which expenses can be delayed without compromising care or compliance.
9. Risk register and milestones
Create a living table:
| Risk | Early warning | Prevention | Contingency | Owner |
|---|---|---|---|---|
| Construction delay | Permit/vendor milestone slips | Weekly dependency review | Revised opening sequence | [Role] |
| Credentialing delay | Missing or pending items | Central tracker | Self-pay/launch decision reviewed | [Role] |
| Hiring gap | Candidate pipeline below need | Earlier recruiting | Adjusted schedule | [Role] |
| Cash shortfall | Downside runway falls | Weekly cash forecast | Funding/cost action plan | [Role] |
| Technology outage | Failed test or weak support | Acceptance testing | Documented downtime process | [Role] |
Tie funding draws and hiring to verified milestones rather than hope. Review the register weekly before opening and monthly after stabilization.
Assemble the lender and adviser package
Keep a controlled folder with the current plan, owner résumé, licenses, entity documents, personal financial information requested by the lender, market evidence, site documents, lease or letter of intent, vendor quotes, construction plan, equipment list, funding request, projections, tax returns as requested, and assumption register.
The SBA notes that business plans may use a traditional detailed format or a lean format depending on the need. Ask the lender what it expects. Keep sensitive files access-controlled and do not email an unprotected package broadly.
Review and update the plan
Review the dental practice business plan template at each major decision: site selection, lease, financing, construction, hiring, credentialing, opening, and the first quarterly review. Update assumptions rather than preserving a forecast that reality has disproved. The value of the plan is not predicting perfectly; it is making decisions visible early enough to act.